By Alejandro Olloqui Escalona (Licensed Gynecologist – 282867126).

The length of an in vitro fertilisation (IVF) treatment cycle depends on the protocol recommended for each patient. Generally, ovarian stimulation takes around 10 to 12 days, while a complete IVF cycle involving a fresh embryo transfer and pregnancy test can take approximately 3 to 5 weeks.
However, not every patient will follow the same timeline. The duration of treatment depends on several factors, including how the ovaries respond to stimulation, the treatment protocol, embryo development and whether the embryo transfer takes place in the same cycle or at a later stage.
It is also important to remember that these estimates do not include the initial fertility assessment or any waiting time before treatment begins. The IVF process can be divided into several stages: cycle preparation, ovarian stimulation, egg collection, fertilisation and embryo culture, embryo transfer, and the waiting period before the pregnancy test.
The first step is to assess each patient's individual circumstances so that the medical team can develop a personalised treatment plan tailored to their needs. This may involve several tests, including hormone blood tests, infectious disease screening, a pelvic ultrasound scan and an assessment of ovarian reserve. Depending on the patient's circumstances, additional investigations relating to sperm quality, the uterus, or their medical and reproductive history may also be required.
Based on these results, the medical team will determine the most appropriate ovarian stimulation protocol, the medication required and when treatment should begin. The duration of this stage can vary considerably. In some cases, the assessment can be completed within a few days, while others may need to wait until their next menstrual cycle or undergo further tests before starting treatment.
Ovarian stimulation usually begins around day 2 or 3 of the menstrual cycle. During this stage, the patient administers daily hormone injections prescribed by the medical team to encourage the growth of multiple ovarian follicles. This phase typically lasts 10 to 12 days, although it may be slightly shorter or longer depending on how the ovaries respond to the medication.
Throughout stimulation, regular ultrasound scans are carried out to monitor follicle growth and adjust medication doses when necessary. These monitoring appointments help the medical team determine the best time to administer the trigger injection, which induces the final maturation of the eggs before collection. Egg collection is usually scheduled approximately 34 to 36 hours after the trigger injection.
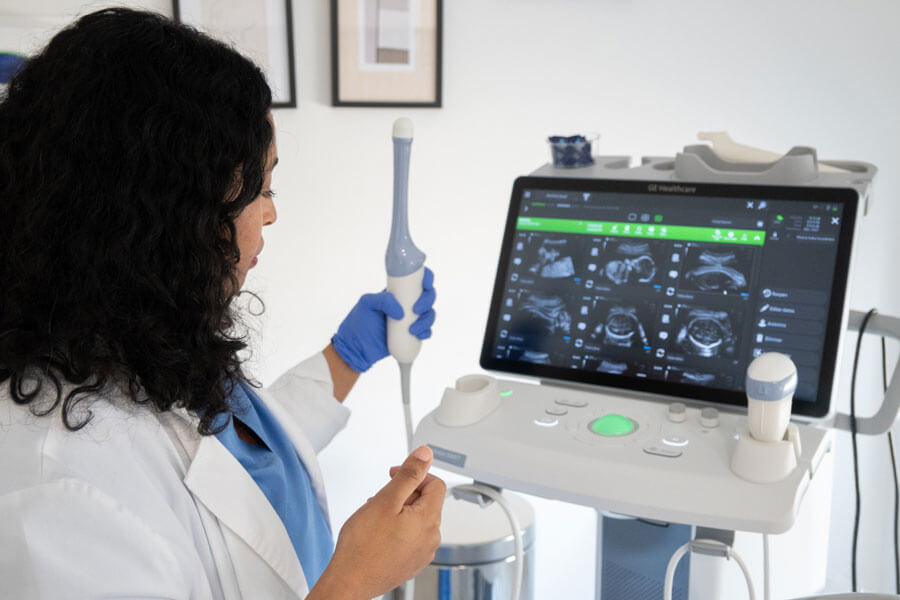
Once the follicles have reached the appropriate stage of development, medication is administered to trigger the final maturation of the eggs, and the egg collection procedure is scheduled. During egg collection, the eggs are retrieved from the ovarian follicles using a fine needle guided by ultrasound. The procedure is performed under sedation, and patients can usually return home the same day.
The mature eggs collected may be frozen or taken to the embryology laboratory for fertilisation using the most appropriate technique for each case. This may involve conventional IVF or intracytoplasmic sperm injection (ICSI), a procedure in which an embryologist injects a single sperm directly into an egg.
In certain circumstances, such as fertility preservation treatments, unfertilised eggs may be vitrified for future use. When embryo transfer is postponed, the embryos obtained are usually vitrified instead. The day after fertilisation, embryologists check how many eggs have fertilised normally. The resulting embryos are then cultured in the laboratory for several days while their development is carefully monitored.
Embryo culture is often continued until the blastocyst stage, which is generally reached on day 5 or 6 of development. This means that, when embryos are cultured to the blastocyst stage, approximately 5 to 6 days usually pass between egg collection and the point at which embryos suitable for potential transfer or vitrification become available. Not all embryos will develop to the blastocyst stage.
Embryo transfer is usually a straightforward procedure in which an embryo is carefully placed inside the uterus using a very fine catheter. After the transfer, the patient enters what is commonly known as the two-week wait (2WW): the period between embryo transfer and the pregnancy test.
When a fresh embryo transfer is performed, it takes place a few days after egg collection, during the same treatment cycle, provided that both the clinical conditions and embryo development are suitable. The exact timing of the pregnancy test depends on the treatment protocol and the developmental stage of the embryo at transfer.
In general, the test is scheduled approximately 10 to 14 days after embryo transfer. Therefore, when the entire treatment takes place within the same cycle, the period from the start of ovarian stimulation to receiving the pregnancy test result is usually around 3 to 5 weeks.
It is important to follow the clinic's instructions regarding when to take the pregnancy test, even if you choose to use a home urine pregnancy test.
So far, we have described the timeline for an IVF cycle involving a fresh embryo transfer, which takes place a few days after egg collection. However, embryos may also be vitrified (frozen) and transferred at a later date for a variety of reasons.
In these cases, the overall treatment takes longer because an additional stage of endometrial preparation is required before the embryo transfer can take place. There are several reasons why this approach may be recommended:
For this reason, a frozen embryo transfer does not necessarily follow the standard 3-to-5-week IVF timeline. Several weeks or even months may pass between ovarian stimulation and embryo transfer. If a frozen embryo transfer is planned, it is advisable to ask your medical team for a personalised estimate of the overall treatment timeline.
The number of appointments required will vary depending on the patient and their treatment protocol. Before treatment begins, an initial consultation and the necessary fertility investigations will be carried out so that the medical team can develop an appropriate treatment plan.
Once ovarian stimulation has started, several ultrasound scans are needed to monitor the ovaries' response to medication. Patients should therefore expect several monitoring appointments during the approximately 10 to 12 days of ovarian stimulation, as well as visits for egg collection and, where applicable, embryo transfer.
The exact number of appointments depends on the ovarian response and treatment protocol, as some patients may require additional monitoring to adjust medication doses or determine the most appropriate timing for egg collection.
For a personalised estimate based on your circumstances, find out more about our IVF treatment at IVF Spain.
Planning these appointments is particularly important for international patients or those who live some distance from the clinic. Where possible, certain initial consultations or tests can be arranged in advance. However, some stages of IVF treatment require in-person monitoring. For this reason, it is important to allow some flexibility with travel dates before arranging transport or booking flights.
Not everyone's ovaries respond to stimulation at the same rate, and some patients need a few additional days of medication for their follicles to reach the appropriate size before egg collection. This does not necessarily mean that the treatment is not working.
During ultrasound monitoring, the fertility specialist assesses the number and size of the developing follicles and may adjust medication doses if necessary. The aim is to determine the most appropriate time to trigger final egg maturation and schedule egg collection.
There is no single waiting period that applies to everyone. If frozen embryos are available following an IVF cycle, it may be possible to arrange another embryo transfer in a subsequent cycle without repeating ovarian stimulation and egg collection. However, if a completely new IVF cycle is needed, the fertility specialist will review how the patient responded to the previous treatment, their physical recovery and whether any adjustments to the protocol would be beneficial before starting again.
If no embryos remain available, or if additional eggs and embryos need to be obtained, the medical team will assess when another IVF cycle can begin. This decision will take into account the patient's previous ovarian response, physical recovery and whether any changes to the treatment plan are appropriate.
In some cases, another treatment cycle can begin relatively soon, while in others it may be advisable to wait or undergo further investigations before proceeding.
Human Fertilisation and Embryology Authority (HFEA).
In vitro fertilisation (IVF).
.
2016;
Guía de la autoridad británica de fertilización y embriología sobre el tratamiento de fecundación in vitro:
https://www.hfea.gov.uk/treatments/explore-all-treatments/in-vitro-fertilisation-ivf/
European Society of Human Reproduction and Embryology (ESHRE).
Guideline on Ovarian Stimulation for IVF/ICSI.
.
2025;
Guía clínica de la Sociedad Europea de Reproducción Humana y Embriología sobre la estimulación ovárica en tratamientos de FIV e ICSI:
https://www.eshre.eu/OSGuideline
European Society of Human Reproduction and Embryology (ESHRE).
The Revised guidelines for good practice in IVF laboratories.
.
2026;
Recomendaciones actualizadas de ESHRE sobre las buenas prácticas en los laboratorios de fecundación in vitro:
https://www.eshre.eu/IVFlabs-guideline/
Practice Committee of the American Society for Reproductive Medicine.
Prevention of moderate and severe ovarian hyperstimulation syndrome: a guideline.
.
2024;
230-245
Descripción del enlace (ES): Guía clínica de la Sociedad Americana de Medicina Reproductiva sobre la prevención del síndrome de hiperestimulación ovárica durante los tratamientos de reproducción asistida:
https://www.asrm.org/practice-guidance/practice-committee-documents/prevention-of-moderate-and-severe-ovarian-hyperstimulation-syndrome-a-guideline-2023/
Privacy Policy
IVF-LIFE, hereby informs you of its privacy policy applied to personal data. The use of the website does not imply that the user must provide any information regarding their identity, and cannot be associated with a specific user by the company. In the event that personal data is provided, this data will be collected and used in accordance with the limitations and rights set out in the aforementioned regulation.
WHO IS RESPONSIBLE FOR THE PROCESSING OF YOUR DATA?
DATA CONTROLLER: IVF SPAIN ALICANTE S.L.U (hereinafter IVF-Life)
CIF: B-54973227
Postal Address: Avenida de Ansaldo, no. 13, 03540, Alicante (Alicante)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: Instituto Vasco de Fertilidad (hereinafter IVF-Life)
CIF: B95575874
Postal Address: Avenida de Tolosa, 71-73, 20018 Donostia / San Sebastián (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: IVF Spain Madrid (hereinafter IVF-Life)
CIF: B 85138113
Postal Address: C/ de Manuel de Falla, 6-8, 28036 Madrid (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
WHAT TYPE OF DATA DO WE PROCESS?
Depending on the products, services, or functionalities that you wish to enjoy, we may need to process different types of data. In general, this data will be, depending on the case, the following:
- Your identification data: for example: name, surname, language, country from which you interact with us, contact details, etc.
- Connection, geolocation and navigation data.
- Commercial information if you are subscribed to our newsletter.
- Data about your tastes and preferences.
WHAT IS THE ORIGIN OF THE DATA?
The use of certain services or requests addressed to IVF-LIFE are subject to the prior completion of the corresponding form. All the information provided by the User through the forms on the Portal for the above purposes or any other must be truthful.
To this end, the User guarantees the authenticity of all the data provided and will keep the information provided to IVF-LIFE perfectly up to date so that it corresponds at all times to the User's real situation. In any case, the User will be solely responsible for any false or inaccurate statements made and for any damage caused to IVF-LIFE or third parties because of the information provided.
By clicking on the "send" button on the corresponding form, the User expressly consents to his/her data being used to send professional communications about his/her query by e-mail or by any other means.
However, the User may revoke the consent given and oppose the sending of such communications in each of the communications received or by sending them to the address indicated in this legal notice and enabled for this purpose. Likewise, in each of the communications sent, the procedure for opposing the sending of new professional communications shall be expressly indicated.
Users who provide personal data of other natural persons are obliged to comply, in relation to said data, with all obligations deriving from the data protection regulations in force, and in particular the duty to inform and obtain the consent of the owner of the personal data.
When we request your personal data to provide access to certain website functionalities, we will mark the required fields to ensure the service can be delivered.
Please note that if you choose not to provide us with this data, you may not be able to complete your registration as a user or you may not be able to enjoy those services or functionalities.
For the processing of data, IVF-LIFE adopts the security levels required by current European and national legislation on the Protection of Personal Data. Notwithstanding the above, technical security in a medium such as the Internet is not impregnable and there may be leaks due to the malicious actions of third parties.
Our services are aimed at people of legal age, in the event that some of our services are specifically aimed at minors, IVF-LIFE will request the consent of parents or guardians for the collection of personal data or, where appropriate, for the automated processing of data as set out in current legislation. If the User is a minor, they are required to have the prior consent of their parents or guardians before proceeding to the inclusion of their personal data in the forms on the Website.
Initially, your personal data are provided directly by you, but in certain cases they may originate from centres, referring doctors and public health systems with which there is collaboration.
FOR WHAT PURPOSES DO WE PROCESS YOUR PERSONAL DATA?
Depending on how you interact with our website, we will process your personal data for the following purposes:
To deal with requests or requests that you make through the different means incorporated into our website.
We only process the personal data that is strictly necessary to manage or resolve your request or application.
For marketing purposes
To the extent that you subscribe to our newsletter, your personal data will be used for the periodic sending of company newsletters.
You should remember that you can unsubscribe from the newsletter, at any time and free of charge, by contacting us via the e-mail address of the data controller or by following the instructions that we will provide you with in each of our communications.
For the management of social networks
If you follow us or contact us through the different social networks in which we are present, we will process the data that you provide to us through these for the sole purpose of responding to your messages or comments and managing our contact list.
Usability and quality analysis to improve our services (cookies).
If you access our platform, we inform you that we will process your browsing data for analytical and statistical purposes, i.e. to understand how users interact with our platform and thus be able to make improvements to it. Likewise, we sometimes carry out quality actions and surveys aimed at finding out the degree of satisfaction of our customers and users and detecting those areas in which we can improve.
WHAT IS THE LEGAL BASIS FOR PROCESSING YOUR DATA?
The legal basis that allows us to process your personal data also depends on the purpose for which we process them, so we will find different legal bases under the following purposes:
Attention to requests for information.
The legal basis for the processing of your data is the informed consent to respond to queries raised through the website, forms and other means provided, which implies the prior reading and acceptance of these conditions by the interested party.
Marketing
The legitimate basis for processing your data for marketing purposes is the consent you provide.
Social networking
The basis of legitimacy is the informed consent to respond to queries raised through the social network, as well as the time when you follow us and want to be part of our contact list.
Usability and quality analysis (cookies)
User consent to the use of cookies.
HOW LONG WILL WE KEEP YOUR DATA?
Request for information. We will process your data for as long as it is necessary to deal with your request or request and thereafter 1 year.
Marketing
We will process your data until you unsubscribe or cancel your subscription to the newsletter.
Social media
We will process your data for as long as it is necessary to deal with your request and for as long as you are a follower of our profile.
WILL WE SHARE YOUR DATA WITH THIRD PARTIES?
Personal data will not be transferred or communicated to third parties, except: legal obligation, we obtain your express consent, or we understand that there is a legitimate interest on our part, which will be duly communicated to you.
However, we inform you that we are present in the following social networks: Facebook, LinkedIn, Instagram and YouTube, to keep our followers informed regarding the company's news and services.
You can access these social networks voluntarily and through the links available on the website itself or by accessing directly and on your own from your browser or installed app.
You should know that this website is not responsible for the use of the data that these social networks may make. However, when these data are generated in the social network and derive from an interaction with our website, we will not be held responsible for the use of such data.
In order to consent to our transfer from this website and the processing of your data, you should carefully read the privacy policy of the social network you wish to access:
Facebook: Facebook Privacy Policy
Instagram: Instagram Privacy Policy
LinkedIn: Linkedin Privacy Policy
YouTube: Youtube Privacy Policy
Spotify: Spotify Privacy Policy
In this way, before clicking on the logos of the SS. RR. present on our website, you can inform yourself and make a redirection with prior knowledge of the processing of your data and on a voluntary basis.
Other technological services:
- WhatsApp: WhatsApp Privacy Policy
- Companies of the "IVF LIFE Group" on the legal basis of consent or legitimate interest: Instituto Vasco de Fertilidad S.L.U., with NIF B95575874 and address at Avda Tolosa, 71-73 Donostia (Gipuzkoa), and IVF Spain Madrid S.L., with NIF B85138113 and address at Calle Manuel de Falla, 6-8, 28036 Madrid.
WHAT ARE YOUR RIGHTS WHEN YOU PROVIDE US WITH YOUR DATA?
We undertake to respect the confidentiality of your personal data and to guarantee you the exercise of your rights.
You may exercise them free of charge by sending us an e-mail to our address above, simply by providing proof of identity, the reason for your request and the right you wish to exercise.
If we consider it necessary in order to identify you, we may ask you for a copy of a document proving your identity. In particular, regardless of the purpose or the legal basis on which we process your data, you have the right to:
Ask us for access to the data we hold about you.
Ask us to rectify the data we already hold about you. Please note that by actively providing us with your personal information in any way, you warrant that it is true and accurate and you undertake to notify us of any changes or modifications to it.
Ask us to delete your data to the extent that they are no longer necessary for the purpose for which we need to process them as we have previously informed you, or to the extent that we no longer have the legitimacy to do so.
Ask us to restrict the processing of your data, which means that in certain cases you may ask us to temporarily stop processing the data or to keep it longer than necessary when you may need it. If you have given us your consent to process your data for any purpose, you also have the right to withdraw your consent at any time.
To receive the personal data concerning you that you have provided to us in a structured, commonly used and machine-readable form and to transfer it to another data controller.
Moreover, where the processing of your data is based on our legitimate interest, you also have the right to object to the processing of your data.
Finally, we inform you of your right to lodge a complaint with the relevant data protection supervisory authority, with the Spanish Data Protection Agency.
CHANGES TO THE PRIVACY POLICY
We may change the information contained in this Privacy Policy from time to time. If we do so, we will notify you by various means through the Platform, or we will notify you at your email address when the change in question is significant to your privacy, so that you can review the changes, assess them and, where appropriate, object to or unsubscribe from any service or functionality.
INFORMATION ABOUT COOKIES
We use cookies and similar devices to facilitate your navigation on the Platform, to know how you interact with us and, in certain cases, to be able to show you advertising based on your browsing habits. Please read our Cookie Policy to learn more about the cookies and similar devices we use, their purpose and other information of interest.