
By Álvaro Díez Álvarez (Gynecologist – License No. 282865580).

Ovarian hyperstimulation syndrome is a complication that can occur following ovarian stimulation. However, it is important to distinguish it from a high ovarian response, as a patient may develop many follicles or have a large number of oocytes retrieved without developing the syndrome. For OHSS to be diagnosed, certain symptoms and clinical changes must also be present.
In OHSS, the ovaries become enlarged and the permeability of the blood vessels increases. One of the molecules involved in this process is vascular endothelial growth factor (VEGF). Its activity increases in response to factors such as the hormone hCG and causes some of the fluid normally contained within the blood vessels to move into other areas of the body, particularly the abdominal cavity.
It is this shift in fluid that causes the symptoms of the syndrome. Although OHSS can potentially become a serious complication, current ovarian stimulation strategies allow us to identify patients at greater risk and tailor treatment to considerably reduce the likelihood of severe OHSS. In fact, both ESHRE (European Society of Human Reproduction and Embryology) and ASRM (American Society for Reproductive Medicine) include specific measures for preventing OHSS in their recommendations.
Ovarian hyperstimulation syndrome does not usually develop while the first doses of ovarian stimulation medication are being administered. Instead, it tends to occur in the days following final oocyte maturation and often after egg retrieval has taken place. Depending on when symptoms develop, OHSS is generally classified as either early- or late-onset:
For patients at high risk, preventive strategies such as embryo freezing and deferred embryo transfer can be used. By avoiding pregnancy during the same cycle, the risk of late-onset OHSS can be reduced.
Symptoms depend on the severity of the syndrome. In mild cases, patients may experience some abdominal bloating, discomfort or nausea. As fluid accumulation increases, more pronounced abdominal pain and even vomiting may occur.
However, it is important to remember that some abdominal discomfort following egg retrieval does not necessarily mean that OHSS is present. Symptoms therefore need to be assessed in terms of their severity and progression, together with other clinical findings.
Severity | Common manifestations |
Mild | Abdominal bloating, discomfort or mild abdominal pain, and nausea. |
Moderate | Increased abdominal distension, pain, nausea or vomiting, and fluid accumulation in the abdomen. |
Severe | Significant ascites, reduced urine output, dehydration, blood or kidney abnormalities and, in some cases, breathing difficulties. |
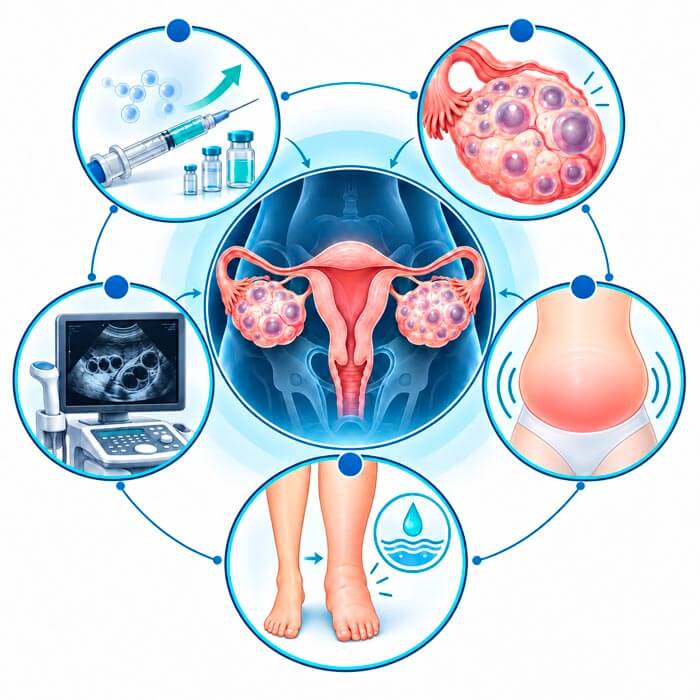
Although severe OHSS can occur, most cases do not progress to a severe form. However, when a substantial amount of fluid moves out of the blood vessels, considerable fluid can accumulate in the abdomen — a condition known as ascites — while the effective circulating blood volume decreases.
When this happens, the blood can become more concentrated, urine output from the kidneys may decrease and electrolyte imbalances may develop. If fluid also accumulates around the lungs, the patient may experience difficulty breathing.
In more severe cases, there is also an increased risk of thromboembolism, in which a blood clot forms and may affect the veins in the legs or the lungs.
Treatment depends on the severity of the condition. There is no medication that can make OHSS disappear immediately once it has developed, so treatment focuses on managing symptoms, maintaining an appropriate fluid balance and preventing potential complications while the body recovers.
In mild cases, outpatient monitoring is usually sufficient, with appropriate hydration according to the medical team's advice and monitoring of how symptoms progress. In moderate cases, ultrasound scans and blood tests may be required to assess the amount of fluid that has accumulated, the degree of haemoconcentration, electrolyte levels and kidney function.
Severe cases may require hospital admission. Treatment may include intravenous fluids, medication to control nausea or pain, and measures to reduce the risk of thrombosis.
When pregnancy has not occurred, symptoms generally improve gradually as ovarian hormonal activity decreases. However, if pregnancy has occurred, the hCG produced during the first few weeks of pregnancy can cause the syndrome to take longer to resolve.
Many assisted reproduction treatments involve ovarian stimulation as part of the process. The aim is to encourage several follicles to develop at the same time so that as many oocytes as possible can be retrieved. This requires the administration of hormonal medication and ultrasound monitoring to assess how the ovaries are responding.
In some patients, however, the ovarian response may be greater than expected. When this response leads to a series of changes in the body, it can result in what is known as ovarian hyperstimulation syndrome (OHSS).
Prevention is a key part of managing the risk of ovarian hyperstimulation syndrome. To reduce this risk, it is important to identify patients who may have a high ovarian response and tailor treatment to their individual characteristics. The main preventive measures include:
A high ovarian response therefore does not necessarily mean that OHSS will develop or that treatment will need to be cancelled. Individualised treatment and appropriate monitoring can substantially reduce the risk while prioritising patient safety.
Ata B, Bosch E, Broer S.
ESHRE guideline: ovarian stimulation for IVF/ICSI: an update in 2025.
.
2026;
498-514
Actualización de la guía de ESHRE sobre estimulación ovárica para tratamientos de fecundación in vitro e ICSI:
https://doi.org/10.1093/humrep/deag018
Practice Committee of the American Society for Reproductive Medicine.
Prevention of moderate and severe ovarian hyperstimulation syndrome: a guideline.
.
2024;
230-245
Recomendaciones basadas en la evidencia para prevenir el síndrome de hiperestimulación ovárica moderado y grave:
https://doi.org/10.1016/j.fertnstert.2023.12.024
Royal College of Obstetricians and Gynaecologists.
The Management of Ovarian Hyperstimulation Syndrome. Green-top Guideline No. 5.
.
2016;
Guía sobre la prevención, diagnóstico y tratamiento del síndrome de hiperestimulación ovárica:
https://www.rcog.org.uk/guidance/browse-all-guidance/green-top-guidelines/the-management-of-ovarian-hyperstimulation-syndrome-green-top-guideline-no-5/
Palomba S, Costanzi F, Nelson SM, Caserta D, Humaidan P.
Interventions to prevent or reduce the incidence and severity of ovarian hyperstimulation syndrome: a systematic umbrella review of the best clinical evidence.
.
2023;
67
Revisión paraguas de la evidencia clínica disponible sobre las intervenciones destinadas a prevenir o reducir la incidencia y gravedad del síndrome de hiperestimulación ovárica:
https://doi.org/10.1186/s12958-023-01113-6
Humaidan P, Nelson SM, Devroey P.
Ovarian hyperstimulation syndrome: review and new classification criteria for reporting in clinical trials.
.
2016;
1997-2004
Revisión del síndrome de hiperestimulación ovárica que propone nuevos criterios de clasificación para su descripción y notificación en ensayos clínicos:
https://doi.org/10.1093/humrep/dew149
Privacy Policy
IVF-LIFE, hereby informs you of its privacy policy applied to personal data. The use of the website does not imply that the user must provide any information regarding their identity, and cannot be associated with a specific user by the company. In the event that personal data is provided, this data will be collected and used in accordance with the limitations and rights set out in the aforementioned regulation.
WHO IS RESPONSIBLE FOR THE PROCESSING OF YOUR DATA?
DATA CONTROLLER: IVF SPAIN ALICANTE S.L.U (hereinafter IVF-Life)
CIF: B-54973227
Postal Address: Avenida de Ansaldo, no. 13, 03540, Alicante (Alicante)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: Instituto Vasco de Fertilidad (hereinafter IVF-Life)
CIF: B95575874
Postal Address: Avenida de Tolosa, 71-73, 20018 Donostia / San Sebastián (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: IVF Spain Madrid (hereinafter IVF-Life)
CIF: B 85138113
Postal Address: C/ de Manuel de Falla, 6-8, 28036 Madrid (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
WHAT TYPE OF DATA DO WE PROCESS?
Depending on the products, services, or functionalities that you wish to enjoy, we may need to process different types of data. In general, this data will be, depending on the case, the following:
- Your identification data: for example: name, surname, language, country from which you interact with us, contact details, etc.
- Connection, geolocation and navigation data.
- Commercial information if you are subscribed to our newsletter.
- Data about your tastes and preferences.
WHAT IS THE ORIGIN OF THE DATA?
The use of certain services or requests addressed to IVF-LIFE are subject to the prior completion of the corresponding form. All the information provided by the User through the forms on the Portal for the above purposes or any other must be truthful.
To this end, the User guarantees the authenticity of all the data provided and will keep the information provided to IVF-LIFE perfectly up to date so that it corresponds at all times to the User's real situation. In any case, the User will be solely responsible for any false or inaccurate statements made and for any damage caused to IVF-LIFE or third parties because of the information provided.
By clicking on the "send" button on the corresponding form, the User expressly consents to his/her data being used to send professional communications about his/her query by e-mail or by any other means.
However, the User may revoke the consent given and oppose the sending of such communications in each of the communications received or by sending them to the address indicated in this legal notice and enabled for this purpose. Likewise, in each of the communications sent, the procedure for opposing the sending of new professional communications shall be expressly indicated.
Users who provide personal data of other natural persons are obliged to comply, in relation to said data, with all obligations deriving from the data protection regulations in force, and in particular the duty to inform and obtain the consent of the owner of the personal data.
When we request your personal data to provide access to certain website functionalities, we will mark the required fields to ensure the service can be delivered.
Please note that if you choose not to provide us with this data, you may not be able to complete your registration as a user or you may not be able to enjoy those services or functionalities.
For the processing of data, IVF-LIFE adopts the security levels required by current European and national legislation on the Protection of Personal Data. Notwithstanding the above, technical security in a medium such as the Internet is not impregnable and there may be leaks due to the malicious actions of third parties.
Our services are aimed at people of legal age, in the event that some of our services are specifically aimed at minors, IVF-LIFE will request the consent of parents or guardians for the collection of personal data or, where appropriate, for the automated processing of data as set out in current legislation. If the User is a minor, they are required to have the prior consent of their parents or guardians before proceeding to the inclusion of their personal data in the forms on the Website.
Initially, your personal data are provided directly by you, but in certain cases they may originate from centres, referring doctors and public health systems with which there is collaboration.
FOR WHAT PURPOSES DO WE PROCESS YOUR PERSONAL DATA?
Depending on how you interact with our website, we will process your personal data for the following purposes:
To deal with requests or requests that you make through the different means incorporated into our website.
We only process the personal data that is strictly necessary to manage or resolve your request or application.
For marketing purposes
To the extent that you subscribe to our newsletter, your personal data will be used for the periodic sending of company newsletters.
You should remember that you can unsubscribe from the newsletter, at any time and free of charge, by contacting us via the e-mail address of the data controller or by following the instructions that we will provide you with in each of our communications.
For the management of social networks
If you follow us or contact us through the different social networks in which we are present, we will process the data that you provide to us through these for the sole purpose of responding to your messages or comments and managing our contact list.
Usability and quality analysis to improve our services (cookies).
If you access our platform, we inform you that we will process your browsing data for analytical and statistical purposes, i.e. to understand how users interact with our platform and thus be able to make improvements to it. Likewise, we sometimes carry out quality actions and surveys aimed at finding out the degree of satisfaction of our customers and users and detecting those areas in which we can improve.
WHAT IS THE LEGAL BASIS FOR PROCESSING YOUR DATA?
The legal basis that allows us to process your personal data also depends on the purpose for which we process them, so we will find different legal bases under the following purposes:
Attention to requests for information.
The legal basis for the processing of your data is the informed consent to respond to queries raised through the website, forms and other means provided, which implies the prior reading and acceptance of these conditions by the interested party.
Marketing
The legitimate basis for processing your data for marketing purposes is the consent you provide.
Social networking
The basis of legitimacy is the informed consent to respond to queries raised through the social network, as well as the time when you follow us and want to be part of our contact list.
Usability and quality analysis (cookies)
User consent to the use of cookies.
HOW LONG WILL WE KEEP YOUR DATA?
Request for information. We will process your data for as long as it is necessary to deal with your request or request and thereafter 1 year.
Marketing
We will process your data until you unsubscribe or cancel your subscription to the newsletter.
Social media
We will process your data for as long as it is necessary to deal with your request and for as long as you are a follower of our profile.
WILL WE SHARE YOUR DATA WITH THIRD PARTIES?
Personal data will not be transferred or communicated to third parties, except: legal obligation, we obtain your express consent, or we understand that there is a legitimate interest on our part, which will be duly communicated to you.
However, we inform you that we are present in the following social networks: Facebook, LinkedIn, Instagram and YouTube, to keep our followers informed regarding the company's news and services.
You can access these social networks voluntarily and through the links available on the website itself or by accessing directly and on your own from your browser or installed app.
You should know that this website is not responsible for the use of the data that these social networks may make. However, when these data are generated in the social network and derive from an interaction with our website, we will not be held responsible for the use of such data.
In order to consent to our transfer from this website and the processing of your data, you should carefully read the privacy policy of the social network you wish to access:
Facebook: Facebook Privacy Policy
Instagram: Instagram Privacy Policy
LinkedIn: Linkedin Privacy Policy
YouTube: Youtube Privacy Policy
Spotify: Spotify Privacy Policy
In this way, before clicking on the logos of the SS. RR. present on our website, you can inform yourself and make a redirection with prior knowledge of the processing of your data and on a voluntary basis.
Other technological services:
- WhatsApp: WhatsApp Privacy Policy
- Companies of the "IVF LIFE Group" on the legal basis of consent or legitimate interest: Instituto Vasco de Fertilidad S.L.U., with NIF B95575874 and address at Avda Tolosa, 71-73 Donostia (Gipuzkoa), and IVF Spain Madrid S.L., with NIF B85138113 and address at Calle Manuel de Falla, 6-8, 28036 Madrid.
WHAT ARE YOUR RIGHTS WHEN YOU PROVIDE US WITH YOUR DATA?
We undertake to respect the confidentiality of your personal data and to guarantee you the exercise of your rights.
You may exercise them free of charge by sending us an e-mail to our address above, simply by providing proof of identity, the reason for your request and the right you wish to exercise.
If we consider it necessary in order to identify you, we may ask you for a copy of a document proving your identity. In particular, regardless of the purpose or the legal basis on which we process your data, you have the right to:
Ask us for access to the data we hold about you.
Ask us to rectify the data we already hold about you. Please note that by actively providing us with your personal information in any way, you warrant that it is true and accurate and you undertake to notify us of any changes or modifications to it.
Ask us to delete your data to the extent that they are no longer necessary for the purpose for which we need to process them as we have previously informed you, or to the extent that we no longer have the legitimacy to do so.
Ask us to restrict the processing of your data, which means that in certain cases you may ask us to temporarily stop processing the data or to keep it longer than necessary when you may need it. If you have given us your consent to process your data for any purpose, you also have the right to withdraw your consent at any time.
To receive the personal data concerning you that you have provided to us in a structured, commonly used and machine-readable form and to transfer it to another data controller.
Moreover, where the processing of your data is based on our legitimate interest, you also have the right to object to the processing of your data.
Finally, we inform you of your right to lodge a complaint with the relevant data protection supervisory authority, with the Spanish Data Protection Agency.
CHANGES TO THE PRIVACY POLICY
We may change the information contained in this Privacy Policy from time to time. If we do so, we will notify you by various means through the Platform, or we will notify you at your email address when the change in question is significant to your privacy, so that you can review the changes, assess them and, where appropriate, object to or unsubscribe from any service or functionality.
INFORMATION ABOUT COOKIES
We use cookies and similar devices to facilitate your navigation on the Platform, to know how you interact with us and, in certain cases, to be able to show you advertising based on your browsing habits. Please read our Cookie Policy to learn more about the cookies and similar devices we use, their purpose and other information of interest.





