By Javier Luna (Registration number – 03622-CV).
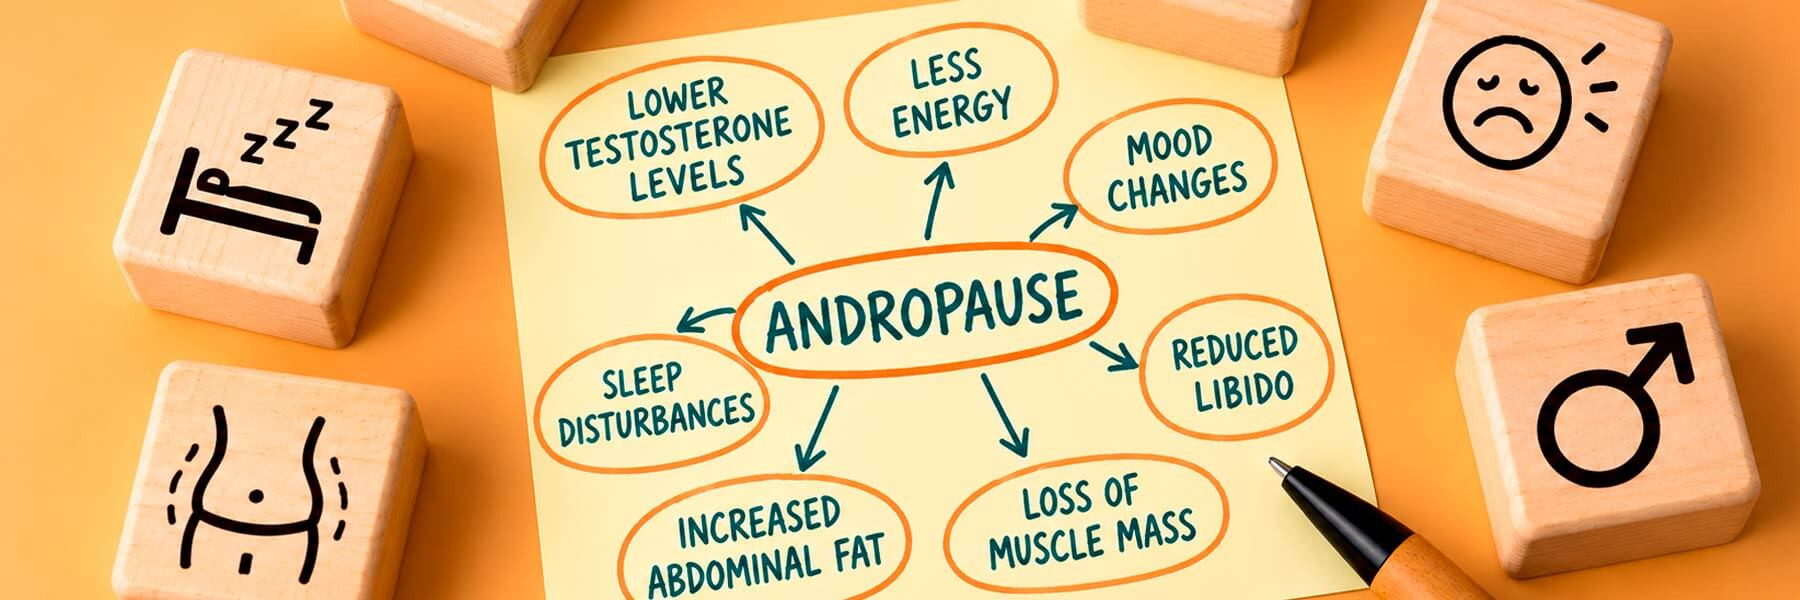
Andropause is a term used to describe the decline in testosterone levels that some men experience with age. Unlike the female menopause, it does not mark the end of fertility. A man with low testosterone levels may continue to produce sperm and can therefore father children naturally or through assisted reproductive techniques.
From a medical perspective, it is more accurate to refer to late-onset hypogonadism or age-related testosterone deficiency.
Men do not stop producing sperm when they reach a particular age. However, ageing can cause hormonal, sexual and reproductive changes that may reduce the chances of achieving a pregnancy.
Testosterone plays a role in functions such as sexual desire, erectile function, muscle mass and bone density and, together with other hormones, in maintaining sperm production.
Testosterone levels may gradually decline with age, although this does not occur in the same way in all men. Other factors can also affect hormone production, including obesity, diabetes, certain medications, sleep disorders and testicular or pituitary conditions.
Therefore, a low testosterone concentration on a blood test is not sufficient to diagnose andropause. Compatible symptoms must also be present.
Symptoms can vary considerably from one man to another. The most common include:
These symptoms can have multiple causes, so a medical assessment is necessary before attributing them to testosterone deficiency.
Diagnosis combines an assessment of symptoms with various hormone tests. Total testosterone is measured using a blood sample taken in the morning. The European Association of Urology (EAU) guidelines state that the diagnosis of male hypogonadism requires compatible symptoms and low testosterone levels confirmed in at least two morning measurements.
Depending on the individual case, hormones such as LH, FSH and prolactin may also be assessed, together with other metabolic parameters. If there is a desire to have children, a semen analysis is particularly important, as it assesses parameters such as sperm concentration, motility and morphology.
Having andropause or low testosterone levels does not necessarily mean that a man is infertile. Unlike female ovarian reserve, sperm production does not suddenly become exhausted at a particular age. Many men continue to produce sperm throughout their lives, although sperm quantity or quality may decline with ageing.
The chances of achieving a pregnancy depend on several factors, including:
For this reason, a man’s fertility cannot be determined solely from his testosterone levels.
Although andropause is sometimes referred to as “male menopause”, the two are distinct processes.
Female menopause | Andropause or late-onset hypogonadism |
Involves the cessation of ovarian function and ovulation. | Does not involve the cessation of sperm production. |
Occurs in all women who reach this stage. | Not all men develop symptomatic testosterone deficiency. |
Marks the end of natural female fertility. | May reduce fertility, but does not necessarily result in infertility. |
Hormonal changes are more pronounced. | Hormonal decline usually occurs gradually. |
One of the most important considerations when a man wishes to become a father is testosterone treatment. It may seem logical to think that administering testosterone to a man with low levels will improve his fertility. However, externally administered testosterone can reduce sperm production.
This occurs because it can suppress the production of LH and FSH, hormones involved in regulating testicular function. As a result, some men may experience a significant reduction in sperm numbers and even temporary azoospermia, meaning an absence of sperm in the ejaculate.
For this reason, the guidelines of the American Urological Association (AUA) and the American Society for Reproductive Medicine (ASRM) recommend carefully assessing the use of exogenous testosterone in men who wish to preserve their current or future fertility. However, other strategies are available to preserve or stimulate testicular function.
As men age, changes may occur in certain semen parameters, as well as an increase in sperm DNA fragmentation. However, these changes do not affect all men in the same way, and there is no specific age at which fertility disappears.
For this reason, sperm DNA fragmentation testing may be considered in situations such as recurrent miscarriage, unexplained infertility, certain previous reproductive failures or specific male-factor conditions.
As long as viable sperm are available, assisted reproductive techniques can help achieve pregnancy, even in cases of andropause or impaired semen quality.
Treatment is selected taking into account both the male and female factors:
Although age-related changes cannot be completely prevented, some factors affecting both hormonal health and semen quality can be modified.
General recommendations include maintaining a healthy weight, engaging in regular physical activity, avoiding smoking and anabolic steroids, limiting alcohol consumption, getting adequate sleep and managing conditions such as diabetes and hypertension.
In general terms, a fertility assessment is recommended after 12 months of regular unprotected sexual intercourse without achieving a pregnancy. Assessment may be brought forward to six months when the woman is aged 35 or over, and it may be appropriate even earlier when there is a history of factors that could affect fertility.
It is also advisable to seek medical advice without waiting when there are factors such as testosterone or anabolic steroid treatment, testicular disease or surgery, previous chemotherapy or radiotherapy, erectile or ejaculatory disorders, or an abnormal semen analysis. The assessment should consider the reproductive situation of both partners together.
European Association of Urology (EAU).
EAU Guidelines on Sexual and Reproductive Health: Male Hypogonadism.
.
2026;
EAU Guidelines on Sexual and Reproductive Health:
https://uroweb.org/guidelines/sexual-and-reproductive-health
European Association of Urology (EAU).
EAU Guidelines on Sexual and Reproductive Health: Male Infertility.
.
2026;
EAU Guidelines on Male Infertility:
https://uroweb.org/guidelines/sexual-and-reproductive-health/chapter/male-infertility
American Urological Association (AUA).
Evaluation and Management of Testosterone Deficiency: AUA Guideline.
.
2018;
AUA Guidelines: Testosterone Deficiency:
https://www.auanet.org/guidelines-and-quality/guidelines
American Urological Association (AUA), American Society for Reproductive Medicine (ASRM).
Diagnosis and Treatment of Infertility in Men: AUA/ASRM Guideline.
.
2024;
AUA/ASRM Guideline on Diagnosis and Treatment of Infertility in Men:
https://www.auanet.org/documents/Guidelines/PDF/2024%20Guidelines/Male%20Infertility%20Unabridged%20Final.pdf
World Health Organization (WHO).
WHO Laboratory Manual for the Examination and Processing of Human Semen.
.
2021;
276
WHO Laboratory Manual for the Examination and Processing of Human Semen:
https://www.who.int/publications/i/item/9789240030787
Privacy Policy
IVF-LIFE, hereby informs you of its privacy policy applied to personal data. The use of the website does not imply that the user must provide any information regarding their identity, and cannot be associated with a specific user by the company. In the event that personal data is provided, this data will be collected and used in accordance with the limitations and rights set out in the aforementioned regulation.
WHO IS RESPONSIBLE FOR THE PROCESSING OF YOUR DATA?
DATA CONTROLLER: IVF SPAIN ALICANTE S.L.U (hereinafter IVF-Life)
CIF: B-54973227
Postal Address: Avenida de Ansaldo, no. 13, 03540, Alicante (Alicante)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: Instituto Vasco de Fertilidad (hereinafter IVF-Life)
CIF: B95575874
Postal Address: Avenida de Tolosa, 71-73, 20018 Donostia / San Sebastián (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
DATA CONTROLLER: IVF Spain Madrid (hereinafter IVF-Life)
CIF: B 85138113
Postal Address: C/ de Manuel de Falla, 6-8, 28036 Madrid (Spain)
Contact with the Data Protection Officer: dpo@ivf-life-group.com
WHAT TYPE OF DATA DO WE PROCESS?
Depending on the products, services, or functionalities that you wish to enjoy, we may need to process different types of data. In general, this data will be, depending on the case, the following:
- Your identification data: for example: name, surname, language, country from which you interact with us, contact details, etc.
- Connection, geolocation and navigation data.
- Commercial information if you are subscribed to our newsletter.
- Data about your tastes and preferences.
WHAT IS THE ORIGIN OF THE DATA?
The use of certain services or requests addressed to IVF-LIFE are subject to the prior completion of the corresponding form. All the information provided by the User through the forms on the Portal for the above purposes or any other must be truthful.
To this end, the User guarantees the authenticity of all the data provided and will keep the information provided to IVF-LIFE perfectly up to date so that it corresponds at all times to the User's real situation. In any case, the User will be solely responsible for any false or inaccurate statements made and for any damage caused to IVF-LIFE or third parties because of the information provided.
By clicking on the "send" button on the corresponding form, the User expressly consents to his/her data being used to send professional communications about his/her query by e-mail or by any other means.
However, the User may revoke the consent given and oppose the sending of such communications in each of the communications received or by sending them to the address indicated in this legal notice and enabled for this purpose. Likewise, in each of the communications sent, the procedure for opposing the sending of new professional communications shall be expressly indicated.
Users who provide personal data of other natural persons are obliged to comply, in relation to said data, with all obligations deriving from the data protection regulations in force, and in particular the duty to inform and obtain the consent of the owner of the personal data.
When we request your personal data to provide access to certain website functionalities, we will mark the required fields to ensure the service can be delivered.
Please note that if you choose not to provide us with this data, you may not be able to complete your registration as a user or you may not be able to enjoy those services or functionalities.
For the processing of data, IVF-LIFE adopts the security levels required by current European and national legislation on the Protection of Personal Data. Notwithstanding the above, technical security in a medium such as the Internet is not impregnable and there may be leaks due to the malicious actions of third parties.
Our services are aimed at people of legal age, in the event that some of our services are specifically aimed at minors, IVF-LIFE will request the consent of parents or guardians for the collection of personal data or, where appropriate, for the automated processing of data as set out in current legislation. If the User is a minor, they are required to have the prior consent of their parents or guardians before proceeding to the inclusion of their personal data in the forms on the Website.
Initially, your personal data are provided directly by you, but in certain cases they may originate from centres, referring doctors and public health systems with which there is collaboration.
FOR WHAT PURPOSES DO WE PROCESS YOUR PERSONAL DATA?
Depending on how you interact with our website, we will process your personal data for the following purposes:
To deal with requests or requests that you make through the different means incorporated into our website.
We only process the personal data that is strictly necessary to manage or resolve your request or application.
For marketing purposes
To the extent that you subscribe to our newsletter, your personal data will be used for the periodic sending of company newsletters.
You should remember that you can unsubscribe from the newsletter, at any time and free of charge, by contacting us via the e-mail address of the data controller or by following the instructions that we will provide you with in each of our communications.
For the management of social networks
If you follow us or contact us through the different social networks in which we are present, we will process the data that you provide to us through these for the sole purpose of responding to your messages or comments and managing our contact list.
Usability and quality analysis to improve our services (cookies).
If you access our platform, we inform you that we will process your browsing data for analytical and statistical purposes, i.e. to understand how users interact with our platform and thus be able to make improvements to it. Likewise, we sometimes carry out quality actions and surveys aimed at finding out the degree of satisfaction of our customers and users and detecting those areas in which we can improve.
WHAT IS THE LEGAL BASIS FOR PROCESSING YOUR DATA?
The legal basis that allows us to process your personal data also depends on the purpose for which we process them, so we will find different legal bases under the following purposes:
Attention to requests for information.
The legal basis for the processing of your data is the informed consent to respond to queries raised through the website, forms and other means provided, which implies the prior reading and acceptance of these conditions by the interested party.
Marketing
The legitimate basis for processing your data for marketing purposes is the consent you provide.
Social networking
The basis of legitimacy is the informed consent to respond to queries raised through the social network, as well as the time when you follow us and want to be part of our contact list.
Usability and quality analysis (cookies)
User consent to the use of cookies.
HOW LONG WILL WE KEEP YOUR DATA?
Request for information. We will process your data for as long as it is necessary to deal with your request or request and thereafter 1 year.
Marketing
We will process your data until you unsubscribe or cancel your subscription to the newsletter.
Social media
We will process your data for as long as it is necessary to deal with your request and for as long as you are a follower of our profile.
WILL WE SHARE YOUR DATA WITH THIRD PARTIES?
Personal data will not be transferred or communicated to third parties, except: legal obligation, we obtain your express consent, or we understand that there is a legitimate interest on our part, which will be duly communicated to you.
However, we inform you that we are present in the following social networks: Facebook, LinkedIn, Instagram and YouTube, to keep our followers informed regarding the company's news and services.
You can access these social networks voluntarily and through the links available on the website itself or by accessing directly and on your own from your browser or installed app.
You should know that this website is not responsible for the use of the data that these social networks may make. However, when these data are generated in the social network and derive from an interaction with our website, we will not be held responsible for the use of such data.
In order to consent to our transfer from this website and the processing of your data, you should carefully read the privacy policy of the social network you wish to access:
Facebook: Facebook Privacy Policy
Instagram: Instagram Privacy Policy
LinkedIn: Linkedin Privacy Policy
YouTube: Youtube Privacy Policy
Spotify: Spotify Privacy Policy
In this way, before clicking on the logos of the SS. RR. present on our website, you can inform yourself and make a redirection with prior knowledge of the processing of your data and on a voluntary basis.
Other technological services:
- WhatsApp: WhatsApp Privacy Policy
- Companies of the "IVF LIFE Group" on the legal basis of consent or legitimate interest: Instituto Vasco de Fertilidad S.L.U., with NIF B95575874 and address at Avda Tolosa, 71-73 Donostia (Gipuzkoa), and IVF Spain Madrid S.L., with NIF B85138113 and address at Calle Manuel de Falla, 6-8, 28036 Madrid.
WHAT ARE YOUR RIGHTS WHEN YOU PROVIDE US WITH YOUR DATA?
We undertake to respect the confidentiality of your personal data and to guarantee you the exercise of your rights.
You may exercise them free of charge by sending us an e-mail to our address above, simply by providing proof of identity, the reason for your request and the right you wish to exercise.
If we consider it necessary in order to identify you, we may ask you for a copy of a document proving your identity. In particular, regardless of the purpose or the legal basis on which we process your data, you have the right to:
Ask us for access to the data we hold about you.
Ask us to rectify the data we already hold about you. Please note that by actively providing us with your personal information in any way, you warrant that it is true and accurate and you undertake to notify us of any changes or modifications to it.
Ask us to delete your data to the extent that they are no longer necessary for the purpose for which we need to process them as we have previously informed you, or to the extent that we no longer have the legitimacy to do so.
Ask us to restrict the processing of your data, which means that in certain cases you may ask us to temporarily stop processing the data or to keep it longer than necessary when you may need it. If you have given us your consent to process your data for any purpose, you also have the right to withdraw your consent at any time.
To receive the personal data concerning you that you have provided to us in a structured, commonly used and machine-readable form and to transfer it to another data controller.
Moreover, where the processing of your data is based on our legitimate interest, you also have the right to object to the processing of your data.
Finally, we inform you of your right to lodge a complaint with the relevant data protection supervisory authority, with the Spanish Data Protection Agency.
CHANGES TO THE PRIVACY POLICY
We may change the information contained in this Privacy Policy from time to time. If we do so, we will notify you by various means through the Platform, or we will notify you at your email address when the change in question is significant to your privacy, so that you can review the changes, assess them and, where appropriate, object to or unsubscribe from any service or functionality.
INFORMATION ABOUT COOKIES
We use cookies and similar devices to facilitate your navigation on the Platform, to know how you interact with us and, in certain cases, to be able to show you advertising based on your browsing habits. Please read our Cookie Policy to learn more about the cookies and similar devices we use, their purpose and other information of interest.